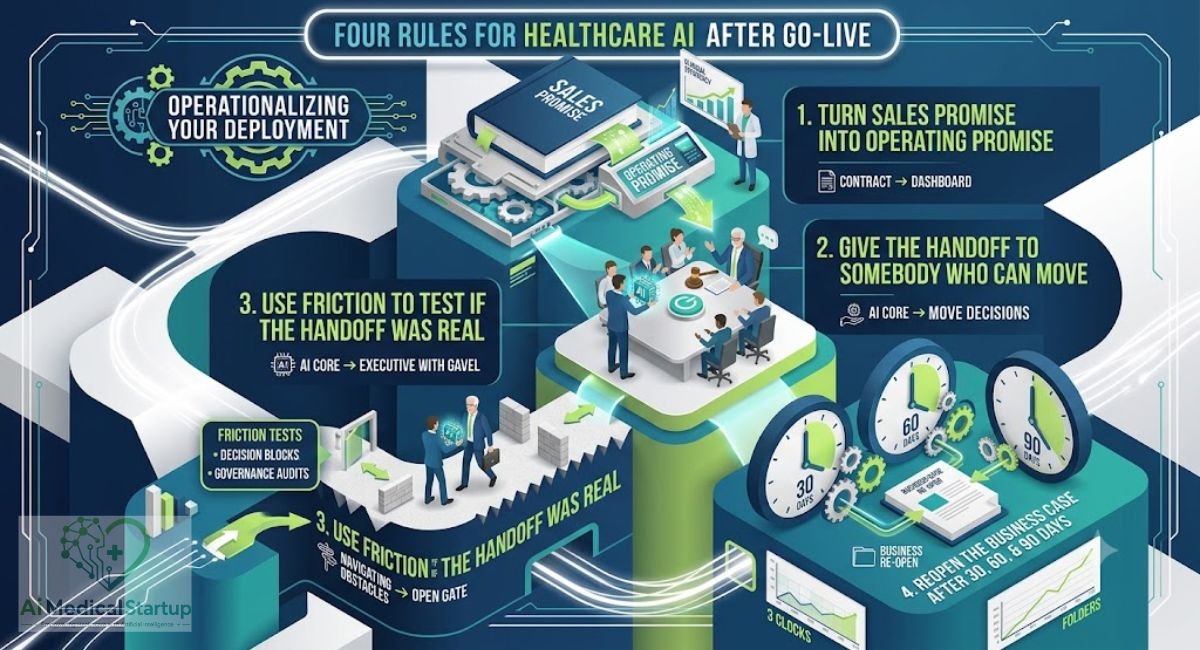
Four Rules for Healthcare AI After Go-Live

The AI Contract Is Signed. Now Who Owns the Outcome?
Four Rules for Healthcare AI After Go-Live
Healthcare organizations can spend months selecting an AI tool and still leave the most important question unanswered: what has to happen after go-live for this thing to change the way the organization actually operates?
The demo looked good. Security signed off. The contract is done. Training is on the calendar. Then the tool meets a real Tuesday morning. A physician is behind. A nurse has three other priorities. IT has a queue. An operations leader is trying to keep the day moving.
That is the part of AI implementation that gets less attention. The technology may work. The organization still has to make it usable. Research on digital health and AI implementation keeps pointing back to the same basic issue: workflow, leadership, infrastructure, training, stakeholder engagement, and local context affect whether technology is actually used. The practical question is what a healthcare organization does with that after the purchase.

Turn the sales promise into an operating promise
“Save time,” “improve decisions,” and “reduce administrative burden” are reasons to buy something. They are not implementation plans.
Before rollout, take the reason the organization bought the AI and make it specific enough to observe. What is supposed to change in the work? Who should feel the difference? What would count as evidence that the promise actually showed up?
Measure the net time saved after review and manual correction steps are fully included.
Identify exactly which decision should move faster and explicitly name who owns it.
Name the specific manual handoff process that should disappear entirely post go-live.
This sounds basic, but it is where a lot of implementations get slippery. A tool can be technically live while the original business case stays vague enough that nobody can tell whether it worked. The vendor can show that the product functions. The healthcare organization still has to define what better work looks like on its side.
Healthcare AI usually crosses more functions than the person who bought it.
Name one implementation owner on the healthcare side and make the decision path clear. That person does not need to control every department, but they need access to the people who do. They also need a way to escalate issues that cannot be solved at the project level.
Clinical buy-in belongs here too. It should not be a presentation after the important decisions are finished. Put real users in front of the proposed workflow early enough that their objections can still change something.
- • Where would you skip this step on a busy day?
- • What would make you distrust the output?
- • What will create duplicate work?
- • Who gets stuck if this part of the process is late?
Use friction to test whether the handoff was real
After go-live, recurring friction is one of the fastest ways to see whether the implementation handoff actually worked.
Corrections, overrides, duplicate entry, ignored alerts, extra clicks, recurring support questions, and workarounds are not all the same problem. Some point to the product. Some point to the workflow. Some point to training, staffing, policy, integration, or a decision nobody has the authority to make.
That matters even more in healthcare because the answer cannot be “the AI said so.” Human review, escalation, and professional judgment have to be built into the operating path, not added after something goes wrong.
Go-live is a date. It is not proof that the investment worked.
The first few months should test the original reason the organization bought the technology. Keep the scorecard small enough that somebody will actually use it.
Are the intended users actually using it?
Is the work faster, simpler, or more reliable after the new steps are included?
How often are users correcting, overriding, bypassing, or escalating the output?
Is the clinical, operational, financial, or staff outcome that justified the purchase moving in the right direction?
Those measures have to be read together. High use can hide a bad workflow if people are required to use the tool. Positive feedback can hide reliability problems. Good technical performance can mean very little if the output arrives too late to matter.
- Specific about the workflow
- Clear about ownership
- Willing to learn from friction
- Disciplined enough to check the business case post go-live
That is not the flashy part of AI. It is the part that decides whether the technology becomes useful work or another expensive system sitting beside the real work.
References
- Hassan, M., Kushniruk, A., & Borycki, E. (2024). Barriers to and facilitators of artificial intelligence adoption in health care: Scoping review. JMIR Human Factors, 11, e48633.
- Preti, L. M., Ardito, V., Compagni, A., Petracca, F., & Cappellaro, G. (2024). Implementation of machine learning applications in health care organizations: Systematic review of empirical studies. Journal of Medical Internet Research, 26, e55897.




Steve DeWitt works across healthcare commercialization, strategic accounts, implementation, and organizational execution. His writing focuses on what happens after technology is purchased: adoption, ownership, workflow, and whether expected value actually shows up in day-to-day work.