
Top 7 Breakthrough Drugs for Ulcerative Colitis Treatment Oct 2026 Updates

Drugs for Ulcerative Colitis Treatment
Ulcerative colitis can turn ordinary days into a cycle of abdominal pain, urgent bathroom visits, and unpredictable flare-ups. Although there is no established cure through medication, modern therapies give many patients a better chance of controlling intestinal inflammation and maintaining ulcerative colitis remission. The evolving ulcerative colitis treatment landscape includes targeted inflammatory pathways, biologic therapies for ulcerative colitis, oral ulcerative colitis medications, and investigational ulcerative colitis treatments designed to address different immune-mediated inflammatory diseases.
However, not every promising medicine has regulatory approval from agencies like the FDA or EMA. This guide explores conventional ulcerative colitis therapies alongside emerging UC therapies, explaining how they work, what clinical trial research suggests, and where uncertainty remains. Although the title highlights breakthrough drugs for ulcerative colitis, the article also reviews additional candidates from your requested list for a broader picture of ulcerative colitis treatment innovations and long-term disease management.
The US accounted for the highest number of diagnosed prevalent ulcerative colitis cases, accounting for half of the total cases of Seven major markets (7MM) in 2025.
Ulcerative Colitis Epidemiology Insights
Ulcerative colitis prevalence has increased substantially across many industrialized regions, creating a growing need for effective long-term disease management and care. This chronic form of Inflammatory bowel disease (IBD) affects the lining of the colon and rectum. Symptoms range from mild diarrhoea to persistent rectal bleeding, fatigue and severe abdominal discomfort. Ulcerative colitis epidemiology varies across populations, while environmental influences, immune dysfunction and genetic susceptibility contribute to disease development.
Across the USA, UK and EU, clinicians classify disease according to its extent, disease activity and impact on daily life. Patients with moderate to severe ulcerative colitis may need advanced treatment when conventional ulcerative colitis therapies fail or lose effectiveness. The Seven major markets (7MM) framework commonly used in pharmaceutical research includes the United States, France, Germany, Italy, Spain, the United Kingdom and Japan. These markets help researchers estimate treatment demand and assess the evolving ulcerative colitis treatment landscape.
Ulcerative Colitis Medications
Choosing among ulcerative colitis medications depends on ulcerative colitis disease severity, previous treatment response, safety and tolerability considerations and patient preferences. Conventional ulcerative colitis therapies include Aminosalicylates, Corticosteroids and Immunomodulators, while advanced options include biologics and small-molecule inhibitors. Induction therapy for ulcerative colitis aims to control intestinal mucosal inflammation, whereas ulcerative colitis maintenance therapy helps preserve sustained remission. Doctors may also consider treatment history, infection risks and extraintestinal complications before selecting an appropriate gut-selective therapy.
The growing range of new ulcerative colitis medications reflects progress in understanding targeted inflammatory pathways. Anti-TNF therapy, IL-23 inhibitors, S1P receptor modulators and Janus kinase (JAK) inhibitors offer different approaches to controlling intestinal inflammation. Newer candidates explore TYK2 inhibitors, TL1A inhibitors and miR-124 enhancement. These advanced ulcerative colitis therapies may expand future choices, but investigational ulcerative colitis treatments require rigorous placebo-controlled clinical trials before regulatory bodies like the FDA or EMA can authorize routine use.
SIMPONI
SIMPONI contains Golimumab, a monoclonal antibody that blocks Tumor necrosis factor-alpha (TNF-alpha). This inflammatory protein can intensify immune activity and contribute to intestinal mucosal inflammation and tissue damage. By reducing TNF signaling, golimumab helps control symptoms in eligible adults with moderately to severely active ulcerative colitis. It is administered by Subcutaneous administration, making it a practical option for patients who need ulcerative colitis maintenance therapy outside an infusion centre.
Among established ulcerative colitis drugs, golimumab may help reduce rectal bleeding, stool frequency and other signs of active disease. However, clinicians must assess infection risks, vaccination status and other relevant medical factors before prescribing it. Its ulcerative colitis safety profile requires particular attention to serious infections and other warnings in the prescribing information. It is not suitable for every patient, and treatment response should be monitored over time.
Vedolizumab
Vedolizumab, marketed as ENTYVIO, is a gut-selective therapy and biologic that targets Alpha-4-beta-7 integrin. This molecule helps certain immune cells travel into intestinal tissue. Blocking the interaction reduces immune cell trafficking into the gut and can limit Intestinal mucosal inflammation. Unlike systemic anti-TNF-alpha therapy, vedolizumab focuses more specifically on the intestinal immune pathway, making it an important option in modern biologic therapies for ulcerative colitis.
Clinical trials have established vedolizumab as a colitis treatment option for eligible adults with moderately to severely active ulcerative colitis. Doctors may consider it when conventional ulcerative colitis therapies or other advanced drugs for UC have not worked adequately. Treatment can involve Intravenous administration or subcutaneous formulations, depending on the product and treatment stage. As with other Monoclonal antibodies, clinicians monitor infections, treatment response and adverse effects while assessing whether the medicine achieves meaningful ulcerative colitis symptom control and mucosal healing.
Etrasimod (APD334)
Etrasimod, originally developed by Arena Pharmaceuticals and known as APD334, is an oral ulcerative colitis medication that modulates the Sphingosine 1-phosphate (S1P) receptor. It acts on S1P receptor subtypes 1, 4 and 5, influencing how lymphocytes move between lymphoid tissues and circulation. This action can reduce the number of certain inflammatory immune cells reaching the intestinal lining. Etrasimod offers an alternative to injectable biologics for appropriately selected patients.
The Food and Drug Administration (FDA) approved etrasimod for eligible adults with moderately to severely active ulcerative colitis, while the European Medicines Agency (EMA) has also authorized its use in the EU. The treatment may help induce and maintain clinical remission, but it requires careful assessment of contraindications and precautions. Clinicians consider heart rhythm, infections, liver function and other label-specific concerns. Patients should follow prescribed monitoring rather than assuming that oral administration carries fewer risks.
SKYRIZI
SKYRIZI contains Risankizumab, an antibody that blocks Interleukin-23 (IL-23), a signaling protein involved in immune-mediated inflammatory diseases. This targeted mechanism distinguishes it from anti-TNF therapy such as golimumab. By inhibiting IL-23, risankizumab can reduce disease activity and help eligible patients achieve clinical remission. Its regulatory approval for ulcerative colitis expanded its role beyond Crohn’s disease, another major form of Inflammatory bowel disease (IBD).
Treatment usually begins with an induction therapy for ulcerative colitis regimen before moving to ulcerative colitis maintenance therapy, according to the approved prescribing information. Certain maintenance regimens allow patients to use an On-body injector at home after appropriate training. Although SKYRIZI represents an important advance among IL-23 inhibitors, its benefits must be balanced against infection risks and other potential adverse effects. A clinician can determine whether its mechanism and dosing schedule fit an individual patient’s treatment needs.
TREMFYA (guselkumab)
TREMFYA, containing Guselkumab, targets IL-23 and has a distinctive mechanism involving binding to CD64, a receptor expressed on certain IL-23-producing cells. This dual action differentiates it from some other Humanized monoclonal antibodies used in inflammatory bowel disease treatment. By targeting a key inflammatory pathway, guselkumab may help control intestinal inflammation and support ulcerative colitis remission in eligible patients with moderately to severely active ulcerative colitis.
Its ulcerative colitis indication and approved dosing options should be checked against the latest regional product information because US and European authorizations can differ. Clinical evidence evaluates induction studies and maintenance studies outcomes, including symptom improvement and endoscopic measures. As with other Biologics, treatment selection depends on previous medications for UC, coexisting conditions and ulcerative colitis treatment safety. The existence of two targeted mechanisms does not automatically prove superior clinical efficacy; reliable head-to-head comparisons would be needed to establish that claim.
Abivax’s ABX464 (Obefazimod)
Abivax’s ABX464, also called Obefazimod, is an investigational ulcerative colitis treatment and small-molecule inhibitor designed to increase MicroRNA-124 (miR-124) expression. This molecule participates in regulating inflammatory responses, making its miR-124 enhancement a different approach from directly blocking a cytokine. The ABTECT induction studies evaluated obefazimod in adults with moderately to severely active ulcerative colitis. In July 2025, Abivax reported positive Phase III clinical trials induction results, strengthening the candidate’s position in the Clinical development pipeline.
The programme has since produced additional maintenance data. In June 2026, Abivax reported that both tested doses met the primary endpoint in its Phase III clinical trials maintenance study, with company-reported clinical remission rates of 50.8% and 51.3%, compared with 10.4% for placebo at Week 44. These are sponsor-reported topline results rather than a guarantee of individual benefit. The company announced plans to submit a US application in late 2026; regulatory approval should not be assumed before regulators complete their review.
Merck’s Tulisokibart
Merck’s Tulisokibart, also known as MK-7240, is an investigational ulcerative colitis treatment antibody targeting Tumor necrosis factor-like ligand 1A (TL1A). This signaling protein is associated with intestinal mucosal inflammation and Intestinal fibrosis. Tulisokibart aims to interrupt this pathway and potentially address inflammatory activity as well as processes linked to tissue remodelling. Its mechanism represents one of the more closely watched novel mechanisms of action in the ulcerative colitis drug development of next-generation ulcerative colitis drugs for IBD.
In June 2026, Merck reported that the Phase III clinical trials ARTEMIS-UC study / ATLAS-UC trial met its primary endpoint of clinical remission at Week 12 and achieved key secondary endpoints. The company also reported a safety profile consistent with earlier Phase II clinical trials. These results are encouraging, but topline findings do not equal regulatory approval. Full data review, further safety assessment and decisions by the FDA and other authorities will determine whether tulisokibart becomes an available ulcerative colitis treatment.
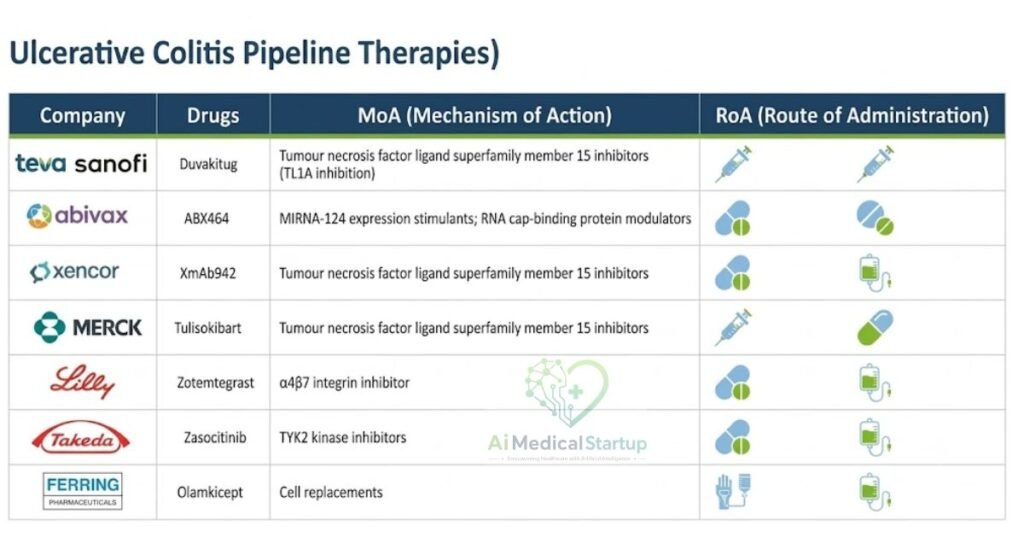
Teva Pharmaceuticals/Sanofi’s Duvakitug
Teva Pharmaceuticals and Sanofi are jointly developing Duvakitug, an investigational monoclonal antibody that blocks TL1A. The target interacts with Death receptor 3 (DR3) and contributes to inflammatory signaling. Duvakitug is designed to inhibit TL1A–DR3 activity while preserving its interaction with Decoy receptor 3 (DcR3). Researchers are investigating whether this approach can reduce intestinal inflammation and potentially limit Intestinal fibrosis in people living with ulcerative colitis or Crohn’s disease.
In February 2026, the companies reported Phase IIb clinical trials maintenance findings showing sustained clinical benefits among patients who had responded to induction therapy for ulcerative colitis. The reported ulcerative colitis remission rates at Week 44 were 58% with the 900 mg dose and 47% with the 450 mg dose. These results apply to the studied population and should not be compared directly with unrelated clinical trials. Phase III clinical trials studies are underway, so duvakitug remains investigational ulcerative colitis treatments rather than an approved medicine.
Eli Lilly’s Zotemtegrast
Eli Lilly’s Zotemtegrast, identified in the supplied competitor material as LY4268989, requires careful name verification before publication. Clinical-trial records identify LY4268989 with MORF-057, an investigational oral alpha-4-beta-7 integrin inhibitor. Its intended mechanism limits the movement of inflammatory lymphocytes into intestinal tissue. This pathway resembles vedolizumab‘s target, although the oral small-molecule inhibitor approach differs from antibody-based biologic therapies for ulcerative colitis.
The Clinical development pipeline programme is assessing safety and tolerability and clinical efficacy in adults with moderately to severely active ulcerative colitis. Researchers are examining outcomes such as clinical remission, ulcerative colitis symptom control and endoscopic response. Because drug codes and development names can change, verify the compound’s official identity against a relevant clinical trial registry before linking it to a company or reporting its phase. It remains important to distinguish an investigational small-molecule inhibitor from an approved colitis treatment option.
Takeda’s Zasocitinib
Takeda Pharmaceuticals’ Zasocitinib, also known as TAK-279, is an investigational ulcerative colitis treatment oral inhibitor of Tyrosine kinase 2 (TYK2). TYK2 helps transmit signals from several cytokines involved in immune regulation, including pathways linked to IL-23. By inhibiting this enzyme, researchers hope to reduce inflammatory activity through a targeted oral ulcerative colitis medication. This strategy differs from antibodies that bind directly to extracellular cytokines or their receptors.
Zasocitinib‘s development status and ulcerative colitis-specific evidence must be verified against current trial records before publication. If studies demonstrate benefit, an oral TYK2 inhibitor could eventually broaden treatment choices for selected patients who need alternatives to injections or infusions. However, potential convenience does not establish superior clinical efficacy or ulcerative colitis treatment safety. Its eventual clinical role will depend on trial outcomes, adverse effects data and regulatory approval decisions rather than its mechanism alone.
Xencor’s XmAb942
Xencor’s XmAb942 is an investigational anti-TL1A antibody developed using the company’s antibody-engineering technologies, including its Xtend Fc domain. By targeting TL1A, the treatment aims to influence inflammatory pathways relevant to ulcerative colitis and Crohn’s disease. The research reflects wider interest in TL1A inhibition as a potential approach to controlling persistent intestinal inflammation and improving long-term disease management.
In May 2026, Xencor reported final Phase I clinical trials data and updates on its development programme. The company is advancing the candidate in the Phase IIb clinical trials XENITH-UC trial, which evaluates efficacy and safety in patients with moderate to severe ulcerative colitis. Researchers must determine whether the treatment improves clinical remission, endoscopic outcomes and safety and tolerability over an appropriate period. Until larger clinical trials provide convincing evidence, claims of best-in-class performance or lasting superiority remain unproven.
Ferring Pharmaceuticals’ Olamkicept
Ferring Pharmaceuticals’ Olamkicept works differently from anti-TNF-alpha therapy and IL-23 treatments. It selectively inhibits IL-6 trans-signaling, a process in which IL-6 binds to a soluble receptor before activating signaling through gp130. This pathway may contribute to intestinal inflammation. Unlike the competitor article’s description of Phase I clinical trials development alone, published research has already examined olamkicept in a randomized Phase II clinical trials trial involving patients with active ulcerative colitis.
The trial, published in JAMA in 2023, investigated treatment response, safety and tolerability compared with placebo. Its findings offer useful evidence but do not establish olamkicept as an approved medicine or confirm its current commercial development status. Before describing it as a leading future option, check the latest sponsor announcements and trial registries. This distinction matters because the Clinical efficacy observed in an early study may not translate into a successful drug for UC for routine clinical practice.
Comparing the Breakthrough Drugs for Ulcerative Colitis Treatment
The following table summarizes the main targets and development stages of the ulcerative colitis medications discussed. It also highlights why the ulcerative colitis medication list should distinguish established FDA-approved ulcerative colitis drugs from investigational ulcerative colitis treatments candidates in the ulcerative colitis treatment landscape.
| Drug | Main Target or Mechanism | Treatment Status |
|---|---|---|
| SIMPONI | TNF-alpha inhibition | Approved for eligible UC patients |
| Vedolizumab | Alpha-4-beta-7 integrin | Approved |
| Etrasimod | S1P receptor modulation | Approved |
| SKYRIZI | IL-23 inhibition | Approved |
| TREMFYA | IL-23 inhibition with CD64 binding | Approved |
| ABX464 / Obefazimod | miR-124 enhancement | Investigational; Phase III clinical trials results reported |
| Tulisokibart | TL1A inhibition | Investigational; Phase III clinical trials results reported |
| Duvakitug | TL1A inhibition | Investigational; Phase III clinical trials underway |
| Zotemtegrast / LY4268989 | Alpha-4-beta-7 integrin inhibition | Verify compound naming and current clinical trial status |
| Zasocitinib / TAK-279 | TYK2 inhibition | Verify current UC-specific Clinical development pipeline status |
| XmAb942 | TL1A inhibition | Investigational; Phase IIb clinical trials programme |
| Olamkicept | IL-6 trans-signaling inhibition | Research stage and current development status require verification |
Frequently Asked Questions (FAQs)
The best medicine for ulcerative colitis depends on ulcerative colitis disease severity, previous treatment response, medical history and personal preferences. Options include Aminosalicylates, biologics, Immunomodulators and targeted oral ulcerative colitis medications. Some patients achieve ulcerative colitis remission with their first treatment, while others need to switch therapies. A Gastroenterology specialist can help select an appropriate option and monitor its clinical efficacy, ulcerative colitis treatment safety, and impact on everyday life.
Several FDA-approved ulcerative colitis drugs are available, including Golimumab, Vedolizumab, Etrasimod, Risankizumab and Guselkumab, alongside other established medications for UC. Approval depends on the drug’s indication, formulation and patient group. For accurate information, consult the FDA Drugs@FDA database and the current prescribing information. European patients should also check the European Medicines Agency (EMA) for relevant regulatory approval authorizations.
Several ulcerative colitis clinical trials are evaluating emerging UC therapies, including Obefazimod, Tulisokibart, Duvakitug and XmAb942. These candidates investigate targeted inflammatory pathways such as miR-124 enhancement and TL1A inhibition. Other research explores LANCL2 protein activation and Toll-like receptor 9 stimulation. Their development stages and results differ, so check ClinicalTrials.gov for current study information and eligibility criteria.
Traditional conventional ulcerative colitis therapies often reduce intestinal inflammation broadly or suppress immune activity. By contrast, some emerging UC therapies target specific molecules or targeted inflammatory pathways. IL-23 inhibitors, TYK2 inhibitors and TL1A inhibitors represent different approaches to modifying inflammatory responses. Nevertheless, a targeted mechanism does not automatically mean fewer adverse effects or greater clinical efficacy. Placebo-controlled clinical trials and comparative studies must establish whether a newer medicine offers meaningful advantages over existing colitis treatment options.
The latest treatment for ulcerative colitis depends on the country and the date of review. Recently approved biologic therapies for ulcerative colitis and oral ulcerative colitis medications have expanded the available choices, while candidates such as Tulisokibart and Obefazimod have reported promising Phase III clinical trials results. However, clinical-trial success is different from regulatory approval. Patients should discuss currently authorized options with their clinicians rather than using an investigational ulcerative colitis treatments candidate outside an appropriate clinical trial.
There is no proven miracle drug for UC that reliably cures Ulcerative colitis. However, many patients can achieve sustained remission and mucosal healing with appropriate long-term disease management and ongoing monitoring. The goal is to achieve ulcerative colitis symptom control, reduce intestinal mucosal inflammation and prevent flare-ups or complications. Because responses vary, personalized medicine and regular follow-up can help clinicians adjust treatment when a medication causes loss of response or unacceptable adverse effects.
Final Thoughts
The topic of breakthrough drugs for ulcerative colitis reflects a rapidly evolving field in Gastroenterology, where established Biologics sit alongside promising experimental investigational ulcerative colitis treatments. Medications for UC targeting Tumor necrosis factor-alpha (TNF-alpha), Interleukin-23 (IL-23), and Sphingosine 1-phosphate (S1P) receptor already provide important choices in the ulcerative colitis treatment landscape. Furthermore, TL1A inhibition and miR-124 enhancement may expand future choices if clinical efficacy and regulatory approval reviews from the FDA and EMA support their routine use.
- For patients living with Ulcerative colitis, the most important outcome is not choosing the newest medicine, but finding a safe and effective ulcerative colitis treatment that controls intestinal inflammation, supports sustained remission, and protects overall ulcerative colitis quality of life.
- For clinicians and researchers, continued ulcerative colitis drug development through Phase III clinical trials will help clarify which advanced ulcerative colitis therapies work best for particular patient groups, allowing personalized medicine to become more precise over time.



Dr. Kanza Sarfraz, M.B.B.S., is a medical doctor and graduate of Allama Iqbal Medical College, Lahore. She brings nearly seven years of clinical experience across tertiary-care hospitals, medical headquarters, and healthcare facilities in both the public and private sectors. Her clinical experience provides a practical perspective on healthcare delivery, emerging medical technologies, and the evolving role of artificial intelligence in medicine.